Where billers still misclassify billable vs non-billable Z codes
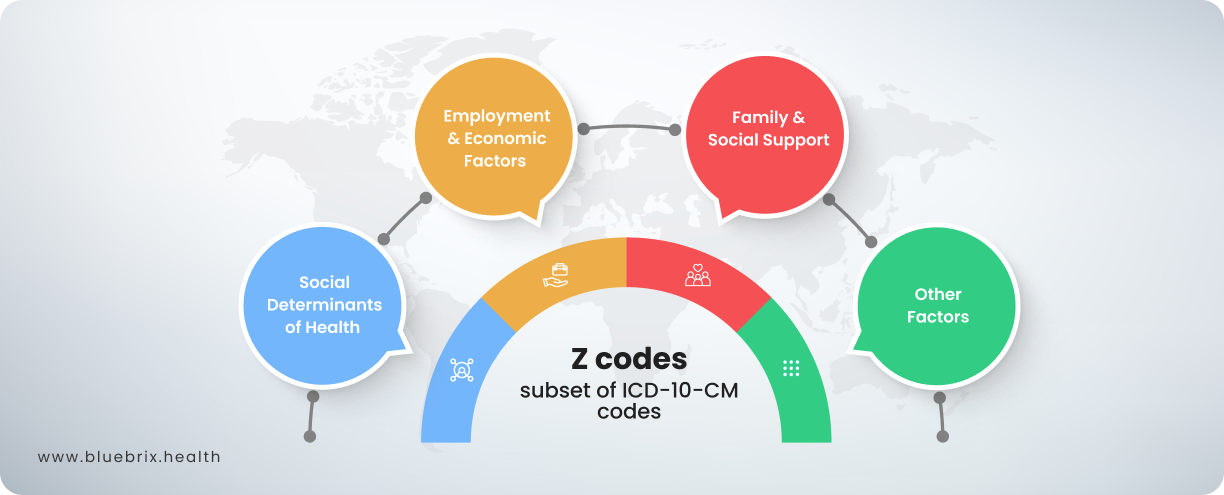
Z codes, the ICD-10-CM codes for status, history, and social circumstances rather than active disease, get treated as a formality on most behavioral health claims: something to add if there’s room, not something that determines whether the claim clears. That assumption is where the denials start. Billable and non-billable status gets confused at the subcategory level, sequencing errors bump a Z code ahead of the clinical diagnosis it’s supposed to support, and SDOH codes that should be capturing real risk data quietly drop out of the intake workflow before they ever reach a claim.
None of this is exotic. It’s the same handful of errors surfacing across behavioral health and SUD billing queues nationwide, and what follows breaks each one down specifically, where the subcategory gets missed, where sequencing trips a payer edit, where SDOH data gets lost between intake and the claim, and what closes the gap in each case.
Z codes for psychotherapy and SUD counseling: the sequencing errors that trigger denials
The recurring pattern in outpatient psychotherapy and SUD counseling claims is a Z code listed ahead of, or in place of, the clinical diagnosis that justifies the encounter. An intake note documents housing instability (Z59.8x) as the primary reason for a counseling session, with the substance use disorder diagnosis relegated to secondary position or omitted entirely. Including the Z code isn’t the problem — leading with it is. ICD-10-CM Official Guidelines Section I.B.14 directs that codes in categories Z55–Z65 be reported as secondary diagnoses only, regardless of what else appears on the claim.[1]
This gets murkier in SUD settings where a single session addresses both the substance use disorder and a documented social stressor tied to relapse risk. Coders default to whichever diagnosis appears first in the note rather than the one that reflects why the service was medically necessary. The fix isn’t a coding rule change, it’s clinician documentation that states plainly which condition drove the treatment decision for that encounter, so the coder isn’t guessing at intent.
One code worth naming directly here: Z71.4x (alcohol and drug abuse counseling) is the Z code most specific to SUD counseling encounters themselves, distinct from the treatment of the substance use disorder diagnosis. Like the other Z categories that can lead a claim, it applies as first-listed only when the encounter’s entire purpose is counseling itself, with no active disorder being treated at that visit; the moment an active SUD diagnosis is also being addressed, that diagnosis leads and Z71.4x moves to a supporting role — the same first-listed logic covered earlier in this piece, applied to the code SUD programs will actually reach for most often.
Can a Z code carry a claim as the primary diagnosis?
Sometimes, but only when the encounter exists solely for the reason the Z code describes. A screening visit with no active symptoms, an aftercare encounter, a preventive counseling session, these can legitimately carry a Z code as the first-listed diagnosis. The moment an active clinical condition is present and being treated, that condition takes precedence, and the Z code moves to secondary position. One group is a hard no regardless of encounter type: the SDOH codes in Z55–Z65 are designated secondary-only, so they never lead a claim even when nothing else is being treated. The table below applies to the other Z categories.
| Can be first-listed (when that’s the whole reason for the visit) | Supporting context only (rarely first-listed) |
|---|---|
| Screening (Z11-Z13) | Personal history (Z85–Z87, incl. Z86.5x) |
| Observation, ruled out (Z03) | Family history (Z80–Z84, incl. Z81) |
| Aftercare (Z43, Z45, Z47-Z49) | |
| Follow-up exam (Z08, Z09) | |
| Preventive/counseling (Z30-Z32, Z69-Z71) | |
| Administrative exam (Z02) | |
| Preprocedural exam (Z01.81x) |
Payer behavior varies here more than the coding guidelines suggest it should. Some commercial plans process Z-code-primary claims for preventive and screening encounters without friction. Others flag them for review by default, treating a Z-code-primary claim as an automatic documentation request regardless of whether the encounter genuinely qualifies. Behavioral health organizations that bill a high volume of screening or aftercare encounters should confirm payer-specific handling before assuming a Z-primary claim will process cleanly, because the guideline being correct doesn’t guarantee the adjudication system agrees.
Z81 vs Z86: the mix-up that's easy to miss on audit
On audit, this shows up as a family history code billed where a personal history code belonged, or the reverse, and it’s rarely caught until a payer or internal auditor pulls the chart and compares the code to the clinical note. Z81 documents a family member’s mental or behavioral disorder history. Z86.5x documents the patient’s own history. Per the ICD‑10‑CM official guidelines, mixing them up doesn’t just risk a technical error, it can misrepresent the patient’s actual risk profile in the record, which matters for care coordination as much as for billing.
The confusion tends to originate upstream of coding, in intake documentation that says something like “family history of alcohol use disorder, patient also affected” without clearly separating the two facts into distinct clinical statements. A coder working from that note has to infer which code applies, and inference is where the swap happens. Clean documentation states each fact separately: the family history as one statement, the patient’s own history as another, so the code selection isn’t a judgment call.
Why aren't SDOH Z codes showing up in behavioral health and SUD claims?
The capture gap forms earlier than the coding step — at intake, where social and behavioral risk factors get discussed and documented in narrative form but never translated into a Z code because the workflow doesn’t prompt for it. A patient discloses food insecurity during a psychosocial assessment. The clinician notes it in the chart. Nobody flags it for coding, because the intake form wasn’t built to route SDOH disclosures into the coding queue the way clinical symptoms are.
There’s a provision in the guidelines that makes this gap more fixable than most teams assume. SDOH codes in Z55–Z65 are among the few in ICD-10-CM that don’t require assignment from the patient’s provider. Per Section I.B.14, they can be coded from documentation by other clinicians involved in the patient’s care — social workers, case managers, community health workers, nurses — as long as that documentation is part of the official medical record.[2]Patient self-reported information also works, provided a clinician or provider signs off on it and incorporates it into the record. The reasoning is that this is social information rather than a medical diagnosis.
For behavioral health organizations, that provision is the whole ballgame. Social risk in these settings is usually surfaced by exactly the roles the rule permits — case managers running a psychosocial assessment, peer specialists, care coordinators. Teams that assume an SDOH code needs a physician or licensed independent practitioner’s diagnostic statement are leaving codable, already-documented data on the table for a requirement that doesn’t apply.
Peer-reviewed data on hospital-level Z-code use bears this out. Between 2017 and 2021, the share of hospitals recording at least one SDOH Z-code climbed from 54.5% to 59.1%, and housing-related codes (Z59.0, Z59.1, and related subcategories) account for nearly all of that volume — 57.7% of hospitals by 2021. The other domains tell a different story. Transportation stayed marginal at 2.4%. Interpersonal safety actually moved backwards, from 5.8% to 5.5%. Food insecurity grew fastest in relative terms, from 0.8% to 8.9%, and utility needs reached 7.9% — real growth, but off a base so close to zero that both remain a rounding error next to housing. All of this despite those domains being screened for and documented in narrative notes far more often than the claims data reflects. Note the scope: this is nonfederal, non-pediatric acute-care hospital data drawn from Medicare fee-for-service claims, so it establishes the industry-wide pattern rather than a behavioral-health-specific rate.[3] Housing gets captured because it’s often tied to a discharge planning workflow that already has a coding trigger built in. The other domains don’t have an equivalent structural prompt, so they fall through even when the clinical documentation exists.
For behavioral health organizations specifically, this shows up as a missed opportunity on two fronts. Claims completeness suffers when documented risk factors never make it onto the claim. And care coordination billing opportunities, cases where a Z code could support a care management or complex case billing code, go uncaptured because the SDOH data never left the narrative note.
42 CFR Part 2: the constraint that sits underneath all of this
Everything above assumes that once a disclosure is documented, it’s safe to route into a codable Z code. For SUD-specific programs, that assumption needs a check first. 42 CFR Part 2 governs what substance-use-identifying information can be disclosed, to whom, and under what consent — independent of what the coding guidelines permit. A patient’s SUD status appearing on a claim is itself a disclosure, and Part 2 constrains that disclosure regardless of whether the Z code or clinical diagnosis is coded correctly.
This matters directly for the structured-intake workflow described above: a field designed to route “SUD-related housing instability” automatically into a billable code also needs to route it only to recipients the patient has consented to disclose to. The design question isn’t only “does this reach the claim cleanly” — it’s “is this specific disclosure, to this specific payer or clearinghouse, permitted under this patient’s consent.” A workflow built purely around coding accuracy, without a Part 2 check built in, can produce a technically correct claim that’s still an improper disclosure.
This is a narrower, more specialized area than general HIPAA compliance, and it’s worth a conversation with legal or compliance counsel familiar with Part 2 specifically before automating any part of this routing — the consent and disclosure rules have enough nuance that general coding guidance, including this article, isn’t the right place to resolve them.
The eleven SDOH Z-code categories, at a glance
| Category | Covers |
|---|---|
| Z55 | Education and literacy problems |
| Z56 | Employment and unemployment problems |
| Z57 | Occupational exposure to risk factors |
| Z58 | Physical environment problems |
| Z59 | Housing and economic circumstances |
| Z60 | Social environment problems |
| Z61 | Negative life events in childhood |
| Z62 | Upbringing-related problems |
| Z63 | Primary support group/family circumstances |
| Z64 | Certain psychosocial circumstances |
| Z64 | Other psychosocial circumstances |
Z61 and Z62 carry disproportionate weight in behavioral health childhood adversity and upbringing-related circumstances are documented constantly in these settings and coded almost never.
How blueBriX addresses this: the gap sits upstream of billing entirely, at the point where a disclosure gets documented, not at the point where a claim gets reviewed. blueBriX platform is configured to support structured SDOH fields at intake, so a disclosure like food insecurity or transportation barriers has a defined place to route into a codable Z code, rather than staying confined to a narrative note that a billing review has no way to reach after the fact.
Why do Z code claims get denied?
Three patterns account for most of what shows up in a Z-code-related denial queue, and they don’t share a fix. Treating all three the same way, typically by just resubmitting with a code added, resolves one of them and leaves the other two denying again.
The standalone-diagnosis denial
A status or history Z code gets submitted with no active clinical diagnosis alongside it. The payer has nothing to adjudicate the service against, since a history code only describes a past fact, not today’s reason for treatment.
Fix: add the missing clinical diagnosis and resubmit. This is the only one of the three that a straight resubmission resolves.
The sequencing denial
A Z code is listed as the primary diagnosis when the encounter clearly involved treatment of an active condition. Most payer systems run automated edits built around first-listed diagnosis rules, and a Z code out of order trips that edit.
Fix: this isn’t a resubmission fix. The code order has to change, and usually the upstream documentation does too, or the same claim denies the same way a second time.
The payer-specific edit
A plan applies a stricter internal rule than the ICD-10-CM guidelines actually require, flagging any Z-code-primary claim for manual review by default, regardless of whether the encounter genuinely qualified.
Fix: not a coding fix at all. This requires knowing that payer’s behavior in advance and building the expected documentation into the claim proactively, since appealing after the denial rarely changes how that plan handles the next one.
Knowing which of the three is driving a given denial is what determines whether the fix is a quick add, a workflow change, or advance knowledge of one payer’s quirks, and misreading which one you’re looking at is usually why the same denial keeps recurring.
What medical necessity documentation for Z codes actually needs to show
The gap that shows up on audit is rarely missing documentation. It’s documentation that gestures at the social or behavioral context without explicitly connecting it to the Z code billed. A note might describe a patient’s housing situation in detail and still fail an audit, because nothing in the note states that the housing instability was a factor the clinician actively addressed or that influenced the treatment plan for that encounter.
Medical necessity for a Z code, particularly an SDOH code used as a secondary diagnosis supporting a care management or complex encounter, needs the note to draw a direct line: this factor was identified, it was clinically relevant to the service provided, and it shaped some part of the treatment decision. A general mention in the social history section of an intake form doesn’t clear that bar on its own. This is where the compliance and documentation side of the organization has real leverage, building note templates that prompt clinicians to make that connection explicit rather than leaving it implied.
What's changing in the 2026-2027 Z code update cycle
The FY2027 ICD-10-CM update takes effect October 1, 2026. CMS and CDC/NCHS have released the updated code files, tabular list, and addenda for the new fiscal year.[4] For behavioral health specifically, the additions this cycle are lighter than last year’s SDOH-focused expansion, and none of them are SUD-specific — so we won’t dwell on them here. What deserves attention instead is a change already in effect from FY2026 that a SUD-focused team is more likely to encounter directly.
CMS and NCHS revised the HIV-related sequencing guidance for FY2026 (effective October 1, 2025), clarifying when to assign Z21 (asymptomatic HIV infection status) versus an active disease code such as B20. This matters more in SUD settings than the update’s general framing suggests: people who inject drugs accounted for 7% of new HIV infections in the US in 2022, per CDC surveillance data, and SUD treatment programs coordinating care for patients with both diagnoses need this sequencing right, not just aware of it.[5] Getting Z21 versus B20 wrong on a claim for a patient in active SUD treatment can misstate their actual clinical status in the record. Organizations still training coders on this FY2026 change should treat it as unfinished business heading into the FY2027 cutover, not something already resolved.
The update cycle creates a second, quieter risk beyond any new codes: claims still going out with codes that were deleted or revised on the prior October 1 cutover. This is usually a systems problem rather than a documentation one. An EHR’s code library that wasn’t refreshed on the effective date will keep offering retired codes as if they’re still valid, and staff select them out of habit because the software hasn’t told them otherwise. The claim then denies on a technicality unrelated to the clinical encounter itself. Confirming the code library reflects the current fiscal year’s guidelines, before the October 1 cutover, not after the first denial shows up, is the cheaper fix here.
Are Z codes reimbursed, and where payers differ?
“Covered by insurance” and “reimbursed” get used interchangeably, but for a Z code, only one of those questions has a straightforward answer. Z codes don’t generate payment on their own, and a claim built around a Z code with no accompanying clinical diagnosis will generally be denied regardless of payer. Where Z codes matter is indirectly, and that indirect impact varies by payer and by program:
- Medicare Advantage / CMS-HCC risk adjustment: SDOH-related Z codes (Z55-Z65) currently carry no HCC weight of their own. Documenting them doesn’t move a patient’s risk score the way a chronic condition code does.[6]
- Some individual payers: A number have started requiring SDOH Z code capture regardless of the lack of HCC weight, as their own internal policy rather than a CMS requirement.
- Value-based and ACO arrangements: Some treat SDOH Z codes differently from standard fee-for-service or Medicare Advantage, using them to inform care coordination billing eligibility even without a direct HCC mapping. Program-level treatment of social risk in ACO quality and benchmarking has been in active flux through the CY2026 rulemaking cycle, so confirm current program rules rather than carrying forward a prior year’s assumption.
One connection worth making explicit: Z codes pair directly with the SUD-specific procedure codes your billing team is already using. An SBIRT screening claim (G0396/G0397 for Medicare, 99408/99409 for commercial, H0049/H0050 for Medicaid) requires a supporting diagnosis code on the claim, like any other Medicare service. CMS instructs providers to report Z71.51 (drug abuse counseling and surveillance) as the primary diagnosis for substance-use counseling and monitoring encounters where no active disorder is being treated.[7] The sequencing and capture rules this article covers apply across SUD claim types — the Z code is the diagnosis side of a claim that also has a procedure side, and getting the diagnosis side right is what determines whether the whole claim holds up.
The takeaway for organizations billing across multiple payer types: treat this as payer-specific due diligence, not a single rule that applies everywhere a Z code shows up on a claim. What a code does for reimbursement under one payer’s program may do nothing under another’s.